
The Nurse Nobody Flags as a Risk
The Nurse Nobody Flags as a Risk
01
Start with a scan.
Most Hospitals Have the Right Infrastructure, Pointed at the Wrong Moment
Most hospitals have already invested in this problem: an EAP, peer support, well-being resources, flexible scheduling where possible, leadership development. None of that is decorative. These systems exist because someone recognized the demands of the job and built infrastructure to respond to them.
So the useful question isn’t why hospitals don’t care. It’s this: if the infrastructure exists, why are capable nurses still quietly disengaging?
The likely answer is that these systems were largely designed around programs, referral, and treatment — resources available once a nurse recognizes she’s struggling and reaches for them. Very few systems are designed for the space before that point, where a nurse is still functioning but the state she’s operating from has started to erode. That’s not a failure of the systems already built. It’s a layer those systems were never designed to cover, and it’s the specific layer Ne Ste Al Frequency Therapy exists to fill.

02
We’re Precise About What Actually Drives a Resignation
Check in.
Turnover has many known drivers: compensation, staffing ratios, scheduling, career progression, leadership quality, geography, family circumstances, retirement. No single factor explains it, and no single intervention resolves it. We’re not going to pretend otherwise.
What’s true within that complexity is narrower and more defensible: sustained, unmanaged stress and disengagement are strongly associated with burnout, and burnout is one of the more consistent predictors of a nurse’s intent to leave. That’s not a claim that removing stress eliminates turnover. It’s a claim that this pathway is real, well-documented, and worth intervening in directly — even while compensation, staffing, and leadership work continues on separate tracks. Our nurse turnover guide covers the full set of causes and costs in more depth.
03
Shift the state.
We Separate Normal Turnover From the Turnover You Can Actually Prevent
Not all turnover is a problem to solve. Some is simply the normal churn of any workforce.
Normal turnover comes from retirement, relocation, and ordinary life changes. Every hospital has this, and it’s healthy.
Avoidable turnover comes from sustained overload, disengagement, and an inability to recover between demands. This is the turnover that compounds understaffing and drives up agency and overtime costs — and it’s largely preventable.
The nurse from the opening isn’t a normal departure. If she leaves, it will likely get filed as a routine exit, when the more accurate explanation is that nobody had a way to notice, mid-shift, that something had already changed for her.
04
We Target Four States, Not a Vague Idea of “Wellness”
See the pattern.
There’s a set of internal states that show up repeatedly in how nurses describe the difference between a sustainable shift and one that erodes them: confidence, calm, motivation, and the ability to hold a boundary.
| State | What It Means for the Nurse |
|---|---|
| Confidence | Trusts her own clinical judgment |
| Colm | Regains composure under pressure |
| Motivation | Reconnects with a reason to keep going |
| Boundaries | Can say no without guilt |
To be precise about what this claim is and isn’t: these aren’t retention metrics, and strengthening them doesn’t guarantee a lower turnover number. They’re conditions worth reinforcing directly, on the premise — and it is a premise, tested per hospital, not asserted as fact — that a nurse who can regularly access these states is better positioned to sustain demanding work over time.
05
We Sit Before Your Existing Systems, Not Instead of Them
We Separate Normal Turnover From the Turnover You Can Actually Prevent
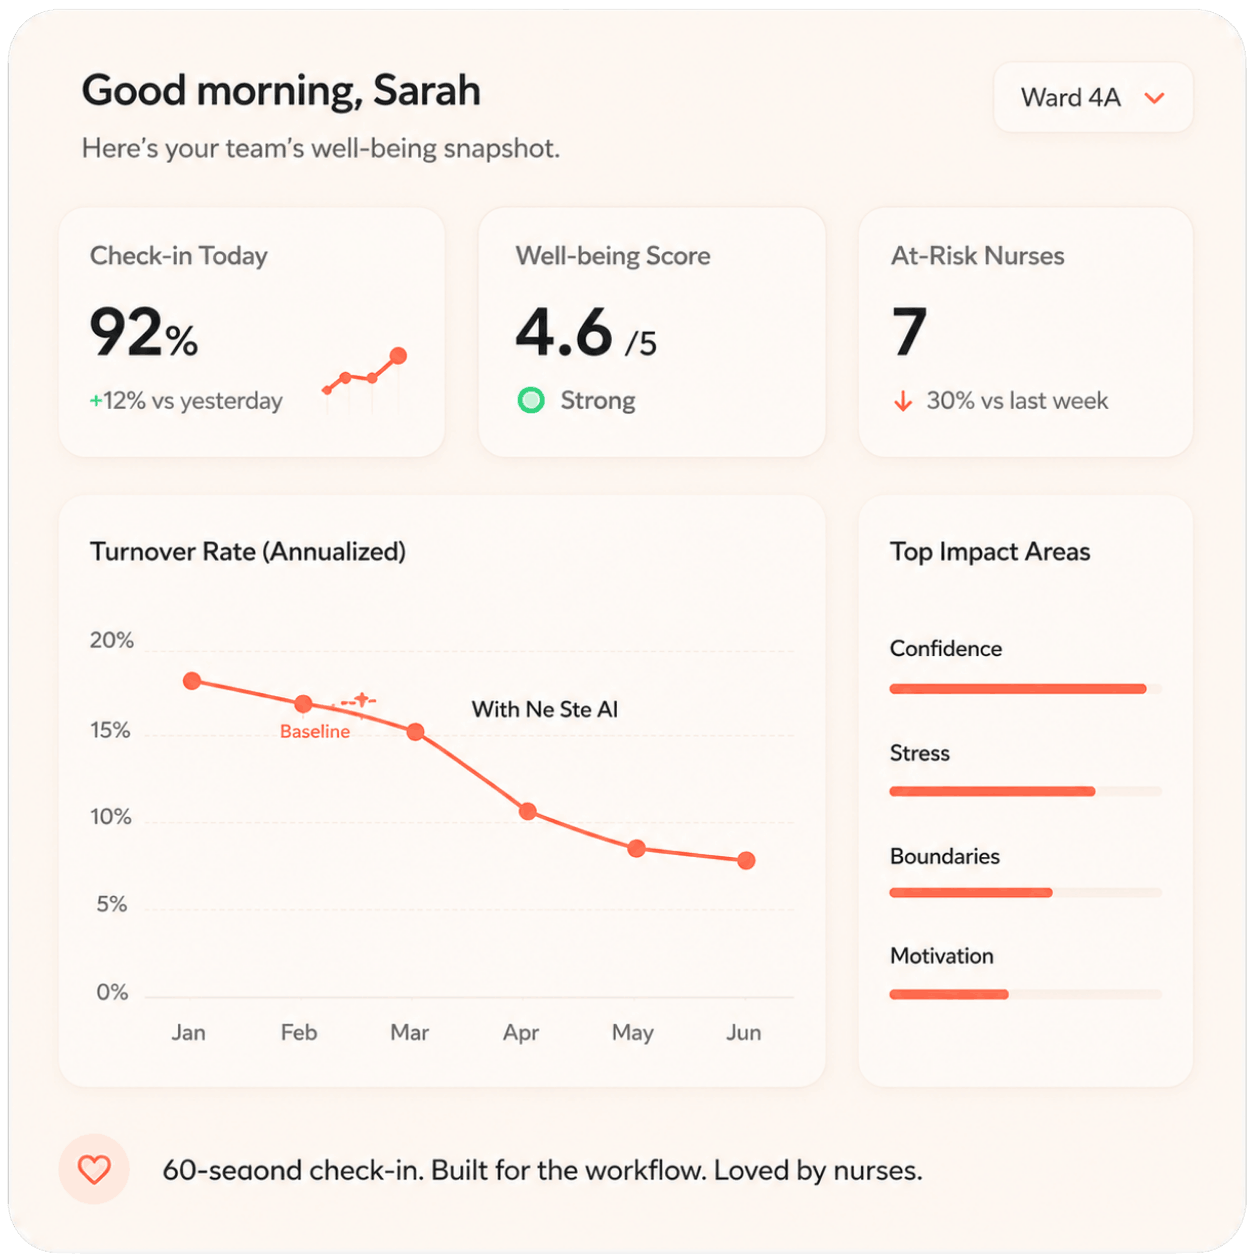
Ne Ste Al is built for the gap between “I’m fine” and “I’m leaving” — not as a replacement for your EAP, clinical care, or escalation pathways, but as a layer that sits before them.
Through Frequency Therapy, a nurse can privately identify the state she wants support with — calm, confidence, motivation, or boundaries — by scanning a unit QR code and completing a short check-in. The request goes to a Ne Ste Al practitioner, who delivers a brief, personalized remote session designed to help shift how she feels in that moment. No app to install, no manager referral, no scheduled appointment.
Frequency Therapy does not diagnose, treat, cure, or prevent any medical or psychiatric condition. It’s a complementary workforce-support layer, designed to work alongside your hospital’s existing clinical care, EAP, and escalation pathways, not in place of them.
06
We Target Four States, Not a Vague Idea of “Wellness”
We Built a Reporting Model Around One Non-Negotiable: Privacy for the Nurse
Leadership never sees an individual nurse’s identifiable responses. Not unit managers, not nursing leadership, not executive leadership, not HR. What leadership sees is aggregated, unit-level reporting: participation, engagement, the states nurses are requesting most, and how those patterns move over time.
That combination is deliberate. Privacy for the individual nurse. Visibility for the organization. It’s also the only structure that makes honest self-reporting possible in the first place — a single leaked exception would quietly collapse trust for an entire unit, so there isn’t one.
07
We’d Rather You Test This Than Believe Us
We Separate Normal Turnover From the Turnover You Can Actually Prevent
We’re not asking hospital leadership to take this on faith, and we wouldn’t want you to. The model is built to be evaluated, not adopted on the strength of an argument.
A pilot starts with one unit, not a hospital-wide rollout. A 10-day activation period gets nurses using the check-in and gives you early engagement data. A 90-day evaluation window, with checkpoints at Day 30 and Day 60, tracks participation and the workforce indicators your hospital agrees matter, measured against a baseline captured on Day 1. At the end, you decide — expand, adjust, or stop — based on what happened on your unit, not on what happened somewhere else.
08
We Target Four States, Not a Vague Idea of “Wellness”
We Didn’t Come From Healthcare, and That’s a Feature, Not a Gap
Ne Ste Al was built by Gaple and Petri, who spent a decade researching burnout and motivation after running a 70-person, £25 million sales organization where even the highest-paid people were arriving on Monday mornings ready to quit. That’s a retention problem, not a healthcare problem — but it’s structurally the same problem hospitals are living with at a much larger scale: capable people, real pressure, and a slow erosion of motivation that eventually ends in a resignation, followed by a vacancy that puts more pressure on everyone left behind.
That decade of research led to Frequency Therapy, developed and applied for more than five years before being adapted specifically for hospital nursing teams. Read more about the people and the story behind it on our About page.
